Endoscopic Management of Full-Thickness Ureteral Perforation Caused by Inadvertent Inflation of a Foley Catheter Balloon Within the Ureter Using Dual Double-J Stenting
DOI:
https://doi.org/10.14740/wjnu1063Keywords:
Foley catheter, Ureteral perforation, Double-J stent, Neurogenic bladder, Iatrogenic injury, UreteroscopyAbstract
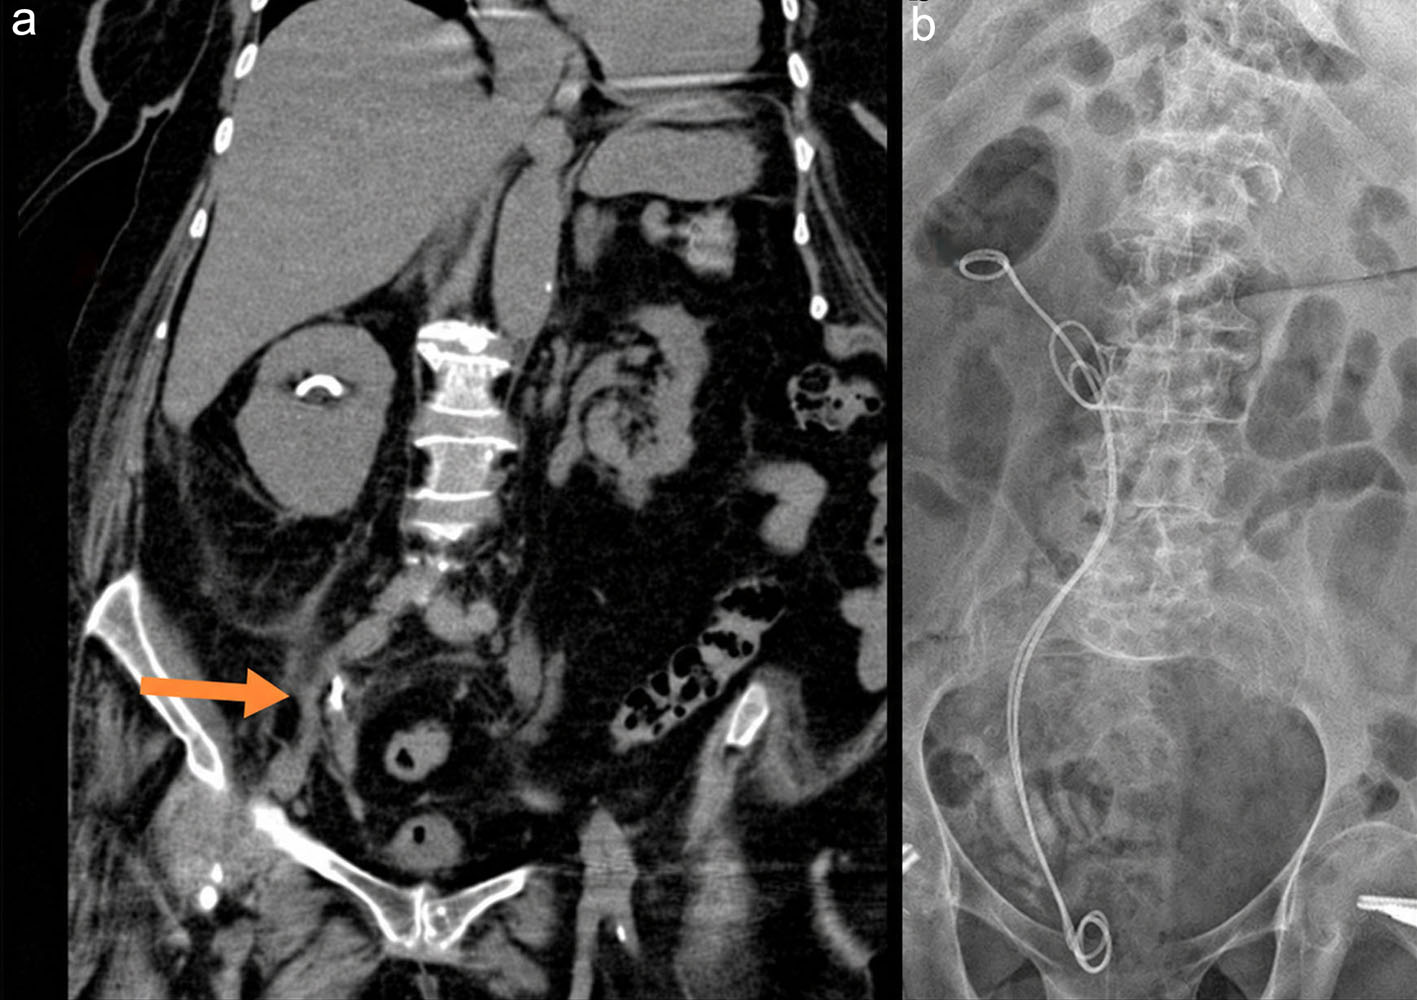
Inadvertent inflation of a Foley catheter balloon within the ureter is a rare but potentially severe complication of urethral catheterization. We report a 68-year-old bedridden woman with advanced Alzheimer’s disease, a clinical diagnosis of neurogenic bladder, markedly reduced bladder capacity, and chronic indwelling catheterization who presented 12 h after routine catheter exchange with right flank pain, fever, and gross hematuria. Non-contrast computed tomography (CT) demonstrated a 16 Fr Foley balloon inflated within the right distal ureter immediately below the iliac vessel crossing. Emergency ureteroscopy showed an approximately 2.5-cm full-thickness defect with complete contrast extravasation. The intact lateral ureteral wall was followed to re-enter the true lumen and obtain renal pelvic access. Two 6 Fr double-J stents were selected intraoperatively because of the extensive defect, relatively wide ureteral lumen, and need for reliable internal drainage; the rationale was to improve luminal stability and preserve drainage if one stent migrated or became obstructed. Percutaneous nephrostomy was reserved for failure of retrograde drainage because collecting-system dilatation was minimal. Clinical and laboratory parameters improved after drainage and antibiotic therapy. Postoperative day 2 imaging showed regression of periureteral inflammation without urinary extravasation, and retrograde pyelography at 6 weeks showed ureteral continuity without leakage before stent removal. No subsequent 3- or 6-month imaging was available because the patient did not return for long-term follow-up. Dual double-J stenting may be a technically feasible option in carefully selected extensive injuries when retrograde true-lumen access and adequate drainage can be achieved, but this single case does not establish superiority over single stenting, nephrostomy, or reconstruction.
Published
Issue
Section
License
Copyright (c) 2026 The authors

This work is licensed under a Creative Commons Attribution 4.0 International License.